

Dual GIP/GLP-1 receptor activity means a single molecule can switch on two of the body’s natural hormone signals at once: GIP (glucose-dependent insulinotropic polypeptide) and GLP-1 (glucagon-like peptide-1). Both hormones help regulate blood sugar, appetite, and how the body handles food. Tirzepatide is the compound researchers have studied most closely for this “two-in-one” approach, while related pathways can be explored with the GLP-2 (TZ) research peptide which is intended for laboratory study only.
Why does it matter? Because understanding how these signals work together helps explain why tirzepatide has drawn so much attention in diabetes and weight research. If you’ve heard the buzz and wondered what’s actually going on under the hood, you’re in good company. Plenty of us in the community, and the allies who love us, want clear answers without a biochemistry degree.
In this guide, we’ll walk through how scientists investigate tirzepatide, from early lab work to clinical trials, and where this research touches everyday life. For personal medical advice, your healthcare provider and Health Canada remain the best sources.
What Dual GIP and GLP-1 Receptor Activity Actually Means
Meet the Two Hormones: GIP and GLP-1
Think of your gut as a quiet messenger service. After you eat, it sends out chemical signals that tell the rest of your body, “food’s arrived, time to get to work.” Two of the main messengers are GIP and GLP-1, part of a family scientists call incretin hormones GIP and GLP-1.
Both help the pancreas release insulin when you’ve eaten, which helps your body handle the sugar from a meal. GLP-1 also nudges appetite signals in the brain, so you feel satisfied sooner and stay that way a bit longer. GIP has its own roles in how the body processes nutrients after eating, and researchers are still working out the finer details.
Here’s a quick glossary of terms you’ll see throughout this article:
- Incretin
- A gut hormone released after eating that helps the body respond to a meal, including prompting insulin release.
- Receptor
- A “lock” on the surface of a cell that a hormone fits into, triggering a response inside that cell.
- Agonist
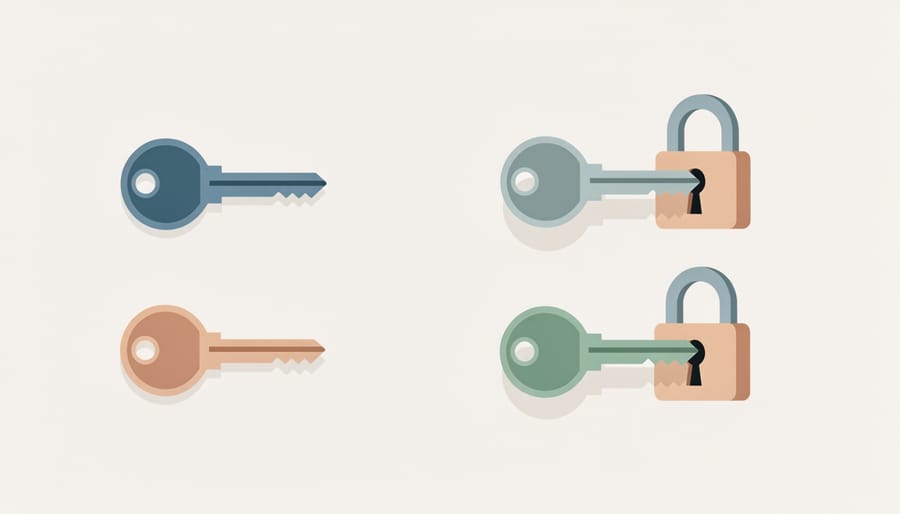
- A substance that switches a receptor on, much like a key turning a lock.
- Dual agonist
- A single medication designed to switch on two different receptors, in this case GIP and GLP-1.
With those basics in hand, the science gets much easier to follow.
Why Researchers Became Interested in Targeting Both
Scientists love a good “what if” question, and this one is a fun one: what if two signals could work together better than one? GLP-1 was already well studied, and medicines built around it had become a major part of research into blood sugar and weight. GIP, by comparison, was the quieter partner. Early on, some researchers wondered whether it was worth pursuing at all.
Over time, though, curiosity grew. Both hormones are released after meals, and both talk to the body’s insulin and appetite systems, but they do it through different receptors. So researchers started asking whether activating both pathways in a single molecule might complement each other.
That idea is the thinking behind tirzepatide’s design. It’s important to say it plainly: this was a hypothesis to test, not a guaranteed outcome. Studies in the lab and in people are how scientists find out whether the idea holds up, and how much it matters.
How Scientists Study Tirzepatide’s Receptor Activity
In the Lab: Testing How Strongly Each Receptor Responds

Before any medication reaches a person, scientists start small, with cells grown in a lab dish. In these cell-based studies, researchers use cells that carry one particular receptor, either the GIP receptor or the GLP-1 receptor. Think of it as setting up two separate locks and testing the same key on each.
When tirzepatide connects with a receptor, it can set off a chain reaction inside the cell. Researchers measure that reaction, often through a chemical signal the cell produces, to see two things: does the receptor switch on at all, and how strongly does it respond as the amount of the molecule goes up?
Running the test on both receptors side by side is the key step. It shows whether the molecule favours one receptor, treats both about equally, or leans somewhere in between. Scientists also compare it to the body’s own GIP and GLP-1 hormones, which gives them a natural benchmark.
This comparison matters because the balance between the two signals shapes how the molecule is understood. Lab results can’t predict exactly what happens in a person, since a dish of cells is much simpler than a human body. That’s why these findings are only the first chapter, and why researchers move on to studies in people next.
In People: Clinical Trials and What They Measure
Once a molecule looks promising in the lab, researchers move on to studies in people. These clinical trials unfold in stages, called phases. Early phases usually involve smaller groups and focus on safety and how the body handles the medicine. Later phases enroll larger and more varied groups to see whether it works as hoped and to keep watching for side effects.
A key feature of many trials is a comparison group. Some participants receive the medication being studied, while others receive a placebo (an inactive look-alike) or a different established treatment. Participants are often randomly assigned, and in many studies neither they nor the researchers know who is getting what. That “blinding” helps keep expectations from coloring the results.
Then there’s the question of what gets measured. In tirzepatide research, common outcomes include blood sugar levels, often tracked through a lab test that reflects average glucose over a few months, and changes in body weight. Researchers also record side effects, since understanding safety matters just as much as understanding benefit.
Findings are typically published in peer-reviewed journals, where independent experts review the work before it appears. If you’re curious, you can look up the trial programs by name, such as the SURPASS and SURMOUNT series, and read the summaries yourself.
Where This Research Shows Up in Real Life
When researchers study how a medication switches on GIP and GLP-1 receptors, the findings don’t stay in the lab. They shape real conversations in clinics, in the news, and around kitchen tables. Understanding that connection can make headlines feel a lot less mystifying.
Here are some of the places where this kind of dual-receptor research shows up:
- Type 2 diabetes management, where receptor studies help explain how a medication may influence blood sugar after meals.
- Weight management, where researchers look at how hormone signals connect to appetite and fullness.
- Ongoing studies into other areas of health, which are still being explored and aren’t settled conclusions.
- Helping readers interpret headlines, since knowing how a study was built makes its claims easier to weigh.
That last point matters more than it might seem. A story that says a drug “works” can mean very different things depending on whether the finding came from cells in a dish, a small early trial, or a large study comparing groups of people over time. Knowing the steps from lab to clinic gives you better questions to ask. Who was studied? What was actually measured? How long did it last? If you’re curious about the thinking behind that kind of questioning, here’s how we approach research when we put stories like this together.
It’s also worth remembering that science keeps moving. What’s approved, who can access it, and what it costs can change, and those details differ from person to person. For current, reliable information, Health Canada is a solid place to start, and your own care provider can talk through what makes sense for your situation.
Reading Health Headlines With Confidence
Health news moves fast, and a single headline can make a study sound like a final answer. A few habits help you read with confidence, and they’re worth sharing with friends and chosen family too.
Start by asking what kind of research you’re looking at. A cell-based lab study, an early human trial, and a large clinical trial each tell you something different. Notice who was studied, how long the study ran, and what was actually measured. Check whether the research appeared in a peer-reviewed journal, and be wary of headlines that promise a miracle or a crisis. When a story feels too good or too alarming, look for the original study or a statement from a trusted health body. Building these habits is one way to counter health misinformation before it spreads through group chats and feeds, much like debunking myths in other areas of community life.
It’s also fair to say that many LGBTQ+ people have run into barriers in healthcare, from feeling misunderstood to avoiding appointments altogether. Being informed won’t fix every gap, but it can make conversations with providers more two-way and respectful. You can bring your questions, ask how research applies to you, and expect to be heard. If a clinic doesn’t feel right, it’s okay to look for an affirming, knowledgeable professional who does.

Common Questions About Tirzepatide Research
A few questions come up again and again when people first read about this research. Here are straightforward answers, in plain language.
What does “dual agonist” mean?
An agonist is a molecule that switches a receptor on, so a dual agonist is a single medication designed to switch on two different receptors. In tirzepatide’s case, those are the GIP and GLP-1 receptors.
How is tirzepatide studied differently from GLP-1-only medications?
Researchers look at the same kinds of outcomes, such as blood sugar and body weight, but they also ask how much of the effect comes from each receptor. That means comparing a dual-acting molecule against ones that target GLP-1 alone.
Are receptor studies the same as clinical trials?
Not quite. Receptor studies usually happen in a lab and measure how strongly a molecule activates a receptor on cells, while clinical trials follow real people over time to see what happens in the body.
Where can I find reliable study information, and should I talk to a provider first?
Peer-reviewed journals, trial registries and Health Canada are good places to start. Because every body and health history is different, it’s worth talking with a care provider you trust before making any decisions.
If you decide to bring questions to an appointment, it helps to jot them down beforehand. Practice makes the conversation easier, and so does learning how to ask better questions that get clear, useful answers. Asking what a study measured, who took part and how long it lasted is a great place to begin.
Understanding how science works is a quiet kind of power. When you know that tirzepatide’s dual GIP and GLP-1 receptor activity is studied step by step, from cells in a lab to carefully designed human trials, headlines start to feel a lot less confusing. You can ask sharper questions, spot hype, and keep your curiosity healthy.
If anything here sparks a personal question, bring it to a healthcare provider who listens and affirms you. And for current, trustworthy information, reputable sources like Health Canada are a great place to start.